
Evolutionary Association, Chapter 2: Fertility
The Dietary Change
Since the 1970s, or the 80s at the latest, when the first dietary guidelines appeared, fat - especially Fatty acids with no reactive molecular component — normally solid at room temperature. Typically animal fats. → more - was considered something “to avoid”, and energy intake was supposed to come mostly from carbohydrates. Meat was to be lean, and if there had to be fats in the food, then at least ones of plant origin. To say nothing of cholesterol - the (new) root of all evil.
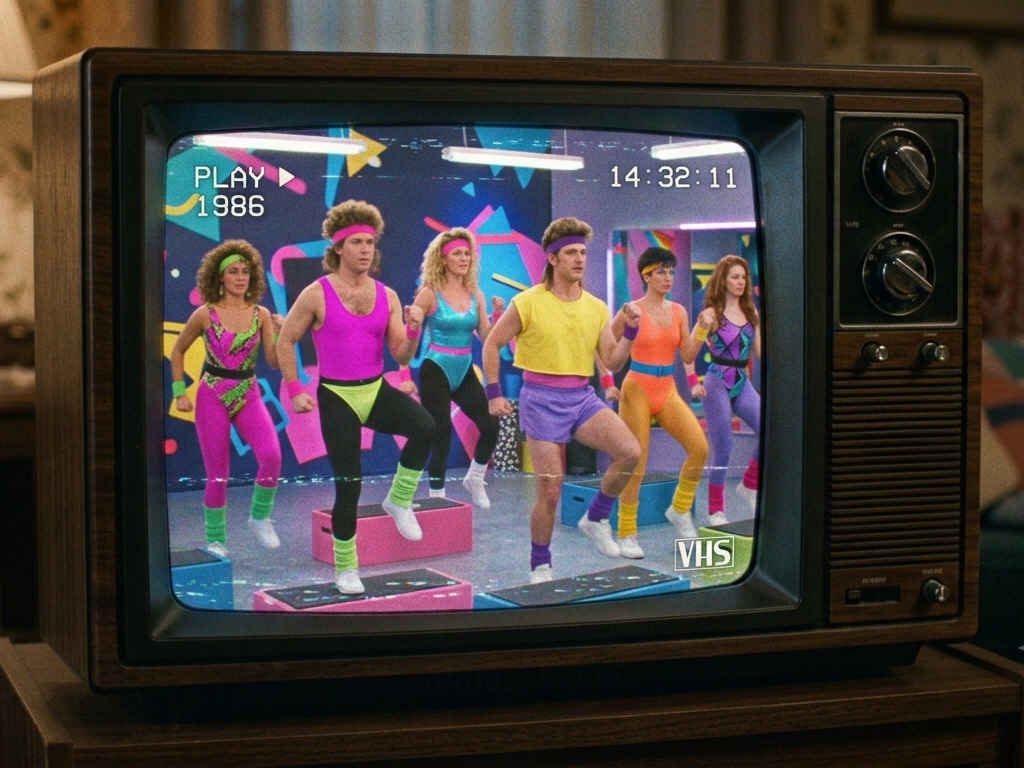
At the same time came the call to excessive exercise. Older readers may still remember very colourful aerobics videos (on VHS, of course, or on linear TV) to follow along with. Younger ones may know them as memes.
I still remember finding it odd that my father liked to take the fattier meat - while I, because I’d hardly known anything else, happily cut the fat off and left it on the plate.
At the same time, diets became popular too - mostly following the principle of calorie balance: if you’d gained weight, you’d probably eaten too much and moved too little. Drastic restrictions of calorie intake - especially for women - became popular, respectable and routine. Magazine crash diets were everyday vocabulary back then, whatever the local brand: Weight Watchers, the cabbage soup diet, the Scarsdale diet - and, in Germany, “Friss die Hälfte” (“eat half”) and “Brigitte-Diät” (named after a popular women’s magazine).
Worth knowing about calorie balance

Caloric Balance: Cause or Effect?
An invitation to reverse the causality: why explaining weight loss through reduced calorie intake is not very helpful
Read more →The Phenomenon
👨 Sperm count and quality
Since the 1970s the male sperm count has fallen by around 50% (1), and testosterone levels have - independently of age - declined by about 1% per year.
For the simultaneous fall in the birth rate there are plenty of other explanations, but since this series is about associations, let me bring one association in early here. (one of those other explanations follows shortly, still in this article)
In fertility, men are needed, but carry a considerably smaller share of the process than women - the main burden of reproduction clearly lies with the woman. On top of that: in women, success and failure are immediately apparent, no matter where the cause lies; in men, only the effort is. So it will surprise no one that there’s considerably more to say about the female side:
👩 Absent menstruation
Personally, I used to hear more often about an almost opposite problem: girls reaching puberty earlier and earlier, and so menstruating earlier and earlier.
What I only came across in the course of my nutrition research is that in more and more women, menstruation sooner or later stops altogether or becomes very irregular - often without medicine being able to help them.
👩 PMS (premenstrual syndrome)
This syndrome comes together with a whole set of other phenomena, among them: irregular cycles, early miscarriages or the inability to become pregnant at all (luteal phase defect).
All these phenomena are related, are now occurring more frequently, and fit well into this collection.
👩 PCOS (polycystic ovary syndrome(2))
Another thing I rarely used to hear about, but which now seems to be occurring explosively: PCOS is today one of the most common causes of infertility, accompanied by acne and a shift in hair growth towards a more male-associated pattern(3).
👩 Follicle quality and egg transport
This is about the poor egg quality that is noticed especially during assisted reproduction (IVF), when the egg can be examined directly. That of course also implies that one has resorted to IVF help in the first place, because a natural pregnancy apparently didn’t come about.
The Biochemical Association
👩👨 sex-independent
First of all: nearly all the observed phenomena can ultimately be explained biochemically (in simplified terms) by the same or a related cause: too little fat intake.
The directly related causes, which I consider related enough to group together here, are: too high a carbohydrate intake (the missing fat has to be made up for by something) and micronutrient deficiency, especially of fat-soluble vitamins.
As a precaution, let me point ahead to the article that will hopefully help clear up any concerns you might have about fat and cholesterol:
Why fat and cholesterol are healthy (and which...)

But Your Cholesterol, Your Heart...
People who hear about a ketogenic diet often wonder whether that much fat can be healthy. The mindset is widespread, but also outdated: the science has moved on.
Instead of tackling each heading from above one by one, I’ll start with a common anecdote:
👨 on the male side
Cholesterol is not a “poison”, but the essential base substrate for all steroid hormones in the human body. Without cholesterol, the Leydig cell in the testis cannot produce testosterone; oestrogen, progesterone and the stress hormone cortisol are based on it too.
At the same time, Fatty acids with no reactive molecular component — normally solid at room temperature. Typically animal fats. → more (SFA) protects the sperm cell membranes from oxidative stress, while a diet rich in unstable Fatty acids with multiple double bonds in the molecule — chemically more reactive than saturated fatty acids. Typically (but not exclusively) plant oils. Omega-3 and omega-6 fall into this category. → more (PUFA) makes sperm more susceptible to oxidative damage. The synchronous course of the demonisation of fat and the hormonal decline of masculinity is striking - an association as if made for this article series.
Another aspect of a PUFA-rich diet we already covered in Chapter 1 of this series:
Chapter 1 of this series

Evolutionary Association, Chapter 1: The Composition of Body Fat
Your love handles are a food diary of the last few years - and many of the entries come from the deep fryer.
Read more →👩 on the female side (a preliminary note)
I absolutely don’t want this section to come across as mansplaining the female body to women. I’m summarising medical studies and diagnoses that I came across in the course of my engagement with a fat-rich diet - like everything here, this is not advice and not a call to action, and cannot replace your own judgement or, where appropriate, medical advice.
Let’s look more closely at the biochemical circumstances of the various phenomena mentioned:
👩 Absent menstruation
The body registers very sensitively whether there’s enough energy and raw material for a pregnancy. After all, that’s an investment of 9 months directly, plus several years afterwards. If it’s clear even before the start that there may not be enough energy even for the pregnancy, it interrupts the processes that would be needed for a pregnancy. One of the molecules needed for this is A hormon that suppresses hunger → more, the satiety hormone. Of all the different kinds of hunger we’ve got to know, it recognises above all the sufficient supply of building materials - that is, proteins and fats - and fuels (does anyone still remember the body’s preferred fuel?). It responds less to fullness, i.e. the physical filling of the stomach and digestive tract with fibre and bulking agents.


When body-fat percentage drops or the acute intake of dietary fat collapses, the leptin level can fall below a critical threshold. The brain interprets this as famine and stops the release of hormones that make a pregnancy possible (5).
Consequence: the cycle comes to a standstill. The body sacrifices fertility to secure its own survival.
👩 PMS (premenstrual syndrome)
Keywords for this, too: “progesterone crash” and “corpus luteum dilemma”.
After ovulation, a follicle transforms into the corpus luteum. This corpus luteum is a veritable hormone factory, which in the second half of the cycle has to produce masses of progesterone (the pregnancy hormone) to maintain the uterine lining.
The corpus luteum has among the highest cholesterol demand of all tissues in the female body. It draws cholesterol directly from the LDL particles in the blood to build progesterone from it.
If the body gets too little fat/cholesterol, the corpus luteum starves biochemically(6). It doesn’t produce enough progesterone, so oestrogen dominates. The uterine lining can’t stabilise, which results in implantation disorders.
👩 PCOS (polycystic ovary syndrome)
Here, for a change, we’re dealing with insulin as the explanation again:
Anyone who replaces fats with refined carbohydrates drives their chronic insulin level up (hyperinsulinaemia). In the ovary, insulin is a massive catalyst. It stimulates the so-called theca cells in the ovary to ramp up the production of androgens (male hormones such as testosterone).
At the same time, the high insulin lowers the liver’s production of SHBG (a protein that binds free testosterone in the blood). The result: the woman becomes biochemically masculinised from the inside out, the follicles no longer mature and remain as “cysts” in the ovary.
Two opposite trenches, the same underlying motif: sometimes too little energy tips the system over (above), sometimes too much insulin (here). At the start, both times, stands the displacement of dietary fat by carbohydrates.
The bitter part: of all things, the low-fat trend was often promoted in the name of a slim body ideal - I saw most of these diets in women’s magazines. That the same path can sensitively disturb the hormonal balance is one of the more unpleasant own goals of this story.
👩 Follicle quality and egg transport
For an egg to mature optimally, the fluid in the follicle needs enormous amounts of antioxidants and fat-soluble vitamins (above all vitamins A and E). They protect the egg’s sensitive DNA from oxidative damage during maturation.
Since these vitamins must necessarily be bound to fat molecules in order to be absorbed in the gut and transported in the blood, an extremely low-fat diet leads to a chronic micronutrient deficiency right in the ovary. The eggs “starve” at the cellular level.
Naturally, with a low-fat diet fewer fat-dissolved vitamins enter the body. And if predominantly plant oils are consumed, carrying the plant forms of these vitamins - which have to be converted rather inefficiently into the bioavailable forms - a deficiency is practically unavoidable and would have to be prevented through targeted supplementation - or, indeed, an adequate diet.
Especially since in the first two cases only the shift from carbohydrates to fat helps - in this case supplementation would help very specifically for this one point, whereas a low-carb/high-fat diet would specifically support all the points.
Fat and cholesterol matter
We can see: fat is, on the one hand, important for hormonal signalling; on the other, it also ensures that important fat-soluble vitamins (which then, admittedly, also have to be present in the fat) get into the body. Cholesterol is not necessarily an enemy to be avoided, but an important building block of many hormones and substances that the body urgently needs for its function.


